

TRAUMA


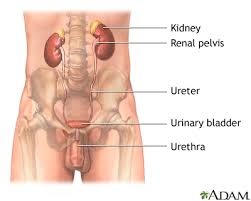


Trauma is defined as the morbid condition of body produced by external violence. Physicians with different specialties evaluate the trauma patient, as a high level of expertise is required. Ten per cent of patients with blunt or penetrating injuries of the abdomen have associated renal trauma.Renal trauma can be acutely life-threatening but the majority of renal injuries are mild and can be managed conservatively.
Patients admitted with severe abdominal injury and shock will need prompt resuscitation and immediate laparotomy. Patients found to have either frank haematuria or microscopic haematuria and clinical shock should be investigated with ultrasound and contrast enhanced computed tomography(CT scan).
The mechanism of renal injuries is classified as blunt or penetrating.Blunt trauma is usually secondary to motor vehicle accidents, falls, vehicle-associated pedestrian accidents, contact sports and assault. Traffic accidents are the major cause for almost half of blunt renal injuries.Renal lacerations and renal vascular injuries make up only 10-15% of all blunt renal injuries.Gunshot and stab wounds represent the most common causes of penetrating injuries. In most cases, they result from interpersonal violence. Renal injuries from penetrating trauma tend to be more severe and less predictable than those from blunt trauma.
Initial assessment of the trauma patient should include securing of the airway, controlling any external bleeding and resuscitation of shock as required.The medical history should be detailed, as pre-existing organ dysfunction has a profound effect on trauma patient outcome. Physical examination is the basis for the initial assessment of each trauma patient. Haemodynamic stability is the primary criterion for the management of all renal injuries.
Ultrasound scans are used in the triage of patients with blunt abdominal trauma, they can be helpful in identifying which patients require a more aggressive radiological exploration to obtain a diagnosis of certainty. . Computed tomography (CT scan) is considered the gold standard method for the radiographic assessment of stable patients with renal trauma. Computed tomography(CT scan) more accurately defines the location of injuries, easily detects contusions and devitalized segments, visualizes the entire retroperitoneum and any associated haematomas, and simultaneously provides a view of the abdomen and pelvis. IVP should be done to establish the presence or absence of one or both of the kidneys, clearly define the renal parenchyma, and outline the collecting system
The goal of management of patients with renal injuries is to minimize morbidity and to preserve renal function. Thus, renal exploration should be undertaken selectively. A life-threatening haemodynamic instability due to renal haemorrhage is an absolute indication for renal exploration, irrespective of the mode of injury. In stable patients, supportive care with bed-rest, hydration and antibiotics is the preferred initial approach. Patients who are treated conservatively carry a risk of presenting with complications later. This risk correlates significantly with increasing grade.
Early complications occur within the first month after injury and can be bleeding, infection, perinephric abscess, sepsis, urinary fistula, hypertension, urinary extravasation and urinoma. Delayed complications include bleeding, hydronephrosis, calculus formation, chronic pyelonephritis, hypertension, arteriovenous fistula, hydronephrosis pseudoaneurysms.
A different approach is needed in children, in whom no correlation between degree of haematuria and severity of injury has been found. Some studies have stated that all children presenting after trauma with haematuria (whether microscopic or macroscopic) should be investigated with computed tomography as the likelihood of important renal injury is greater.
Children are more susceptible to renal trauma than adults. Differences in anatomy and physiology, as well as the higher incidence of pre-existing renal disease, make children more likely to sustain injury.Haematuria is an important clinical sign of renal injury. Ultrasound is considered a reliable method for screening and following the course of renal injury of paediatric patients with blunt renal trauma. Also children may develop accidental zipper entrapment injuries to the penis which may sometimes involve urethra.
URETER INJURIES
Any external injury to the flank or back and any calamity within the bony pelvis therefore places the ureter at risk. Perhaps because of its protected location, its small size and its mobility, trauma to the ureter is relatively rare and accounts for only 1% of all urinary tract trauma.
After gynaecological pelvic surgery, if any woman who complains of flank pain, develops vaginal leakage of urine or becomes septic should also be suspected of having injury to the ureter or bladder and should be investigated appropriately.Ureteral trauma should be suspected in all cases of penetrating abdominal injury Once recognized, they can be managed with ureteral stenting or by placement of a nephrostomy tube to divert urine.
Upper third: Uretero-ureterostomy
Transuretero-ureterostomy
Ureterocalycostomy
Middle third: Uretero-ureterostomy
Transuretero-ureterostomy
Boari flap and reimplantation
Lower third: Direct reimplantation
Psoas hitch
Blandy cystoplasty
Complete: Ileal interposition
Autotransplantation
URINARY BLADDER INJURIES
Lower urinary tract injury may be caused by either blunt, penetrating, or iatrogenic trauma. About 10% of trauma patients will manifest genitourinary tract involvement. About 70-97% of patients with bladder injuries from blunt trauma have associated pelvic fractures Traumatic forces may be transferred to the urinary bladder by the seatbelt and injuries usually occur in the patient with a full bladder. The two most common sign and symptoms are gross haematuria (82%) and abdominal tenderness (62%) in patients with major bladder injuries . Other findings may include the inability to void, bruises over the
suprapubic region and abdominal distension . Extravasation of urine may result in swelling in the perineum,Cystography is accepted as the most accurate radiological study for diagnosing bladder.
Most patients with extraperitoneal rupture can be managed safely by catheter drainage only, Intraperitoneal ruptures occurring after blunt trauma should always be managed by surgical exploration.
URETHRAL INJURIES
The male urethra is divided into the anterior and posterior sections by the urogenital diaphragm. The posterior
urethra consists of the prostatic and the membranous urethra. The anterior urethra consists of the bulbar and
penile urethra. Only the posterior urethra exists in the female;
Injuries to the posterior urethra occur with pelvic fractures, which are commonly caused by road traffic accidents, crush injuries or falls from height.
The severe shearing forces necessary to fracture the pelvis are transmitted to the prostato-membranous junction, resulting in disruption of the prostate from its connection to the anterior urethra at the prostatic apex.
Retrograde urethrography and magnetic resonance imaging have been correlated with this location of the injury . An accurate knowledge of the functional anatomy of the sphincter mechanism is essential to the success of posterior urethral surgery.Thus, clinical management can be advised accordingly:
• Type I no treatment required
• Types II and III can be managed conservately with suprapubic cystostomy (SPC) or urethral catheterisation.
• Types IV and V will require open or endoscopic treatment, primary or delayed.
• Type VI requires primary open repair.
It has been shown that the more proximal the injury, the greater the risk of incontinence, impotence and stricture formation in the long follow up.These can occur involving the urethra, as well as being iatrogenic injuries caused by endoscopic instrumentation or during surgery for vaginal repair.
Another less frequent cause of blunt anterior urethral trauma occurs in association with ruptures of the corpora cavernosa, which usually occur with an erect penis, often during intercourse. In these injuries, the urethra is involved in 20% of the cases.
In females, urethral and bladder neck damageoccur quite often due to ischaemic injury during obstructed labour.
Intraluminal stimulation of the urethra with foreign objects have also been implicated for urethral injuries.Iatrogenic urethral injuries caused by instrumentation are also one of the common causes of urethral trauma.
Urethral ischaemic injuries related to cardiac bypass procedures are not infrequent and can result in long and fibrotic strictures.
In conscious patient, a thorough voiding history should be obtained to establish the time of last urination, force of urinary stream, painful urination and presence of haematuria. Retrograde urethrography is considered the gold standard for evaluating urethral injury . A scout film
should be performed first.
If posterior urethral injury is suspected, a suprapubic catheter is inserted; a simultaneous cystogram and ascending urethrogram can be carried out at a later date to assess the site, severity and length of the urethral injury.The potential early complications of acute urethral injuries include strictures and infections. After the patient has adequately recovered from any associated injuries, and the urethral injury has stabilized, the urethra can be thoroughly re-evaluated radiographically and, when necessary, the appropriate reconstructive procedure planned. It is important to make a distinction between posterior urethral stricture and a subprostatic pelvic fracture urethral distraction defect, as the principles of their surgical management are entirely different. Erectile dysfunction occurs in 20-60% of patients after traumatic posterior urethral rupture. Partial tears of the posterior urethra can be managed in most cases with a suprapubic or urethral catheter.The treatment options available include primary realignment, immediate open urethroplasty, delayed primary urethroplasty, delayed urethroplasty and delayed endoscopic incision.
The incidence of genital trauma is higher in men than in women, not only because of anatomical differences but also due to increased exposure to violence, performance of aggressive sports and motor vehicle accidents. blow to the erect penis may cause penile fracture, frequently occurring during consensual intercourse, the penis slips out of the vagina and strikes against the symphysis
pubis or perineum.
Testicular rupture is found in approximately 50% of blunt traumas to the scrotum. Off-road
bicycling and motorbike riding, especially on bikes with a dominant petrol tank, accidents from in-line hockey skating and rugby footballers have been associated with blunt testicular trauma . Any kind of full contact sports, without the use of necessary protective aids, may be associated with genital trauma.
Besides these risk groups, self-mutilation of the external genitalia have also been reported in psychotic patients and transsexuals .The presence of subcutaneous haematoma, without rupturing of the cavernosal tunica albuginea and no immediate detumescence of the erect penis, does not require surgical intervention.
In the case of penile fracture, immediate surgical intervention with closure of the tunica albuginea is recommended. Blunt trauma to the scrotum can cause significant haematocele without testicular rupture. In cases of testicular rupture, surgical exploration with excision of necrotic testicular tubules and closure of the tunica albuginea is mandatory.
more in blog
more in blog
- RENAL COLICPRIAPISMACUTE URINE RETENSIONSEVERE PALLORABSCESSANIMAL BITESPOISONINGBURNSSEIZURESPARALYTIC STROKEANY PREGNANCY RELATED EVENTSUDDEN LOSS OR IMPAIRMENT OF VISIONSUDDEN HEAD ACHE AND VOMITINGHIGH GRADE FEVERNON-RESPONSIVENESSVIOLENT BEHAVIOURSUDDEN CALF PAINSEVERE BREATHLESSNESS


